Knee Pain Treatment Options Before Considering Knee Replacement
Introduction
Degenerative joint disease represents one of the leading contributors to mechanical disability worldwide. When the protective layers of cartilage lining the femoral condyles and tibial plateau deteriorate, the resulting friction creates inflammation, progressive bone remodeling, and profound functional impairment. While initial management strategies prioritize joint preservation through targeted rehabilitation and pharmacological therapies, severe structural collapse often leaves joint resurfacing as the only dependable solution. Knee replacement surgery is a mature, technically refined orthopedic intervention designed to restore functional alignment, stabilize the limb, and address intractable mechanical pain. Deciding to undergo major orthopedic reconstruction requires an objective understanding of joint mechanics, procedural alternatives, and postoperative commitments. Navigating these clinical choices involves evaluating the extent of joint damage, reviewing implant technologies, and selecting an institution with proven surgical volume and low complication rates. Independent patient education resources such as KneeHospitals.com support this decision-making framework by breaking down complex orthopedic concepts, highlighting modern rehabilitation pathways, and assisting families in identifying specialized surgical centers across both domestic and international treatment networks.
The Biomechanics of Joint Resurfacing
To understand knee arthroplasty, one must evaluate the knee as a tripartite, load-bearing synovial joint. It comprises three distinct anatomical zones:
- Medial tibiofemoral compartment: The interior articulation between the femur and tibia, bearing approximately 60 to 70 percent of ground reaction forces during normal bipedal gait.
- Lateral tibiofemoral compartment: The outer hinge interface, providing rotational balance and lateral shock absorption.
- Patellofemoral compartment: The anterior trochlear groove where the patella glides under mechanical tension generated by the quadriceps mechanism.
In advanced arthritic states, the articular cartilage wearing down leaves subchondral bone unprotected. Rather than removing the biological joint entirely, an orthopedic surgeon executes a biological resurfacing procedure. Using precision cutting blocks or robotic-guided oscillating blades, the surgeon removes a calibrated wafer of bone (typically 8 to 10 millimeters) along with remnants of damaged cartilage.
Cobalt-chromium, titanium, or oxidized zirconium alloy components are then anchored to the prepared bone ends. Between these metallic components sits an ultra-high-molecular-weight polyethylene (UHMWPE) insert. This spacer functions as artificial cartilage, providing a smooth gliding plane and restoring the biological joint space while correcting abnormal joint angulation.
Etiology and Pathomechanics of Joint Degeneration
Articular cartilage possesses virtually no intrinsic vascularity, meaning once structural damage occurs, spontaneous biological repair is minimal. Multiple distinct disease processes drive this deterioration:
- Primary Osteoarthritis: A complex disease driven by mechanical wear coupled with low-grade biochemical degradation of the extracellular cartilage matrix.
- Post-Traumatic Osteoarthritis: Secondary wear that arises following intra-articular fractures, untreated ligamentous instability (such as chronic anterior cruciate ligament deficiency), or prior meniscectomy.
- Autoimmune Arthropathies: Conditions such as rheumatoid arthritis or psoriatic arthritis, where inflammatory synovitis releases proteolytic enzymes that degrade cartilage across all compartments simultaneously.
- Subchondral Osteonecrosis: A localized vascular compromise starving the femoral condyle of perfusion, leading to structural microfractures and subsequent surface collapse.
Contributing risk factors involve biomechanical misalignment (congenital varus or valgus limbs), repetitive high-impact physical loading, endocrine abnormalities, and elevated body mass index, which exponentially increases joint contact pressures during stair climbing and ambulation.
Clinical Indicators Warranting Surgical Assessment
Orthopedic surgeons do not determine surgical candidacy solely on radiographic findings; clinical symptoms must correlate with structural pathology. Patients should seek specialized evaluation when exhibiting:
- Intractable joint line pain that fails to respond to oral NSAIDs, activity modification, or localized injections.
- Night pain and rest discomfort that disrupts restorative sleep cycles.
- Mechanical locking, crepitus, or frequent episodes of the joint buckling under direct axial load.
- Fixed deformities, such as a severe bow-legged (varus) or knock-kneed (valgus) stance that steadily worsens.
- Progressive loss of joint range of motion, particularly a flexion contracture where the knee cannot reach complete zero-degree extension.
The presence of these functional deficits indicates that joint preservation techniques may have reached their biological limit.
The Clinical Diagnostic Workup
Formulating an appropriate treatment strategy requires an objective diagnostic battery:
History and Functional Assessment
The clinician documents walking tolerance, reliance on assistive ambulation devices, stair navigation capacity, and history of conservative interventions.
Objective Physical Examination
The examination assesses active and passive range of motion, neurovascular integrity of the lower leg, presence of joint effusion, collateral and cruciate ligament stability, and extensor mechanism strength.
Radiographic Protocol
- Full-Length Weight-Bearing Bilateral Radiographs: Standing views are non-negotiable. They demonstrate true joint space loss under load, osteophyte formation, subchondral bone sclerosis, and overall mechanical limb alignment.
- Specialized Views (Merchant/Skyline and Lateral): These evaluate patellofemoral tracking and posterior condylar integrity.
- Cross-Sectional Imaging (CT or MRI): Indicated when complex bone loss is present, when planning patient-specific instrumentation, or when excluding occult osteonecrosis.
Conservative Management: Pre-Surgical Optimization
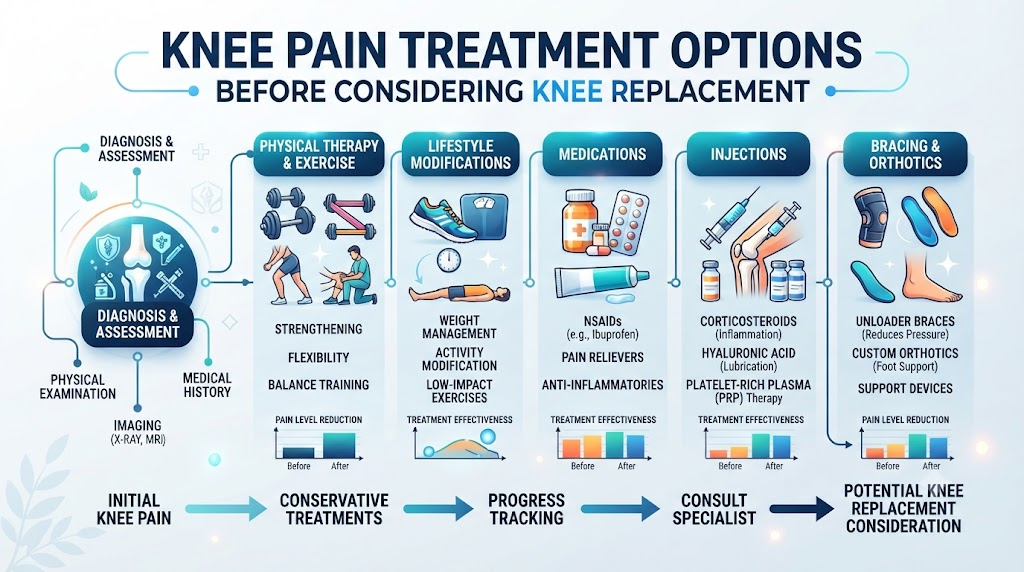
Prior to scheduling joint replacement, standard orthopedic guidelines mandate a thorough trial of conservative, non-operative treatments:
- Targeted Physical Therapy: Structured protocols focused on isometric and closed-kinetic-chain strengthening of the quadriceps, hamstrings, and hip abductors to improve joint stability.
- Biomechanical Offloading: Unloader knee braces that apply an opposing mechanical force to decompress an arthritic medial or lateral compartment.
- Pharmacological Management: Judicious use of oral anti-inflammatories, topical analgesics, and monitored pain relievers.
- Intra-Articular Injections: Corticosteroid injections can quiet active synovial inflammation, while viscosupplementation provides temporary fluid cushion for selected patients with moderate wear.
- Nutritional and Weight Strategies: Lowering total mechanical mass reduces cumulative articular loading throughout daily activity.
When these conservative steps yield diminishing returns and baseline function continues to drop, arthroplasty emerges as the standard intervention.
Surgical Categorization: Total vs. Partial Arthroplasty
The decision regarding surgical approach depends on compartment involvement and anatomical integrity:
Total Knee Replacement (TKR)
Total arthroplasty addresses generalized, multi-compartment arthritis. The surgeon resurfaces the distal femur, proximal tibia, and, when clinically indicated, the posterior patella. Components are secured via polymethylmethacrylate (PMMA) bone cement or specialized porous coatings that permit biological osseointegration.
TKR reliably corrects significant axial deformities, resolves widespread bone-on-bone pain, and provides structural durability for individuals with advanced, multi-compartmental joint deterioration.
Unicompartmental (Partial) Knee Replacement (UKR/PKR)
When disease processes remain strictly confined to a single compartment—typically the medial zone—a partial replacement preserves unaffected bone stock.
Key clinical distinctions include:
- Retention of both the anterior and posterior cruciate ligaments, preserving natural joint mechanics and spatial position awareness (proprioception).
- Reduced intraoperative blood loss and smaller soft-tissue dissections.
- Stringent patient selection: Candidates must exhibit intact cruciate ligaments, absence of significant angular deformity, and zero active inflammatory arthritis.
Surgical Protocols, Safety, and Hospital Management
Modern orthopedic facilities rely on standardized, fast-track clinical pathways to enhance patient safety:
Preoperative Optimization
Patients undergo comprehensive cardiac and pulmonary clearance, screening for metabolic stability, and dental evaluations to eliminate potential focal points for hematogenous prosthetic infections.
Anesthesia and Surgery
Procedures are typically conducted under neuraxial (spinal) anesthesia paired with targeted ultrasound-guided peripheral nerve blocks (such as adductor canal blocks). This approach minimizes systemic narcotic use, reduces postoperative nausea, and facilitates early ambulation. The operative time typically spans 60 to 90 minutes.
Inpatient Care
Physical therapists initiate gait training within hours of surgical completion. In modern settings, patients transition home on the day of surgery or complete a brief one-to-two-night stay focused on pain modulation, independent transfers, and wound checks.
Risk Management
While modern surgical infection controls and advanced techniques maintain low adverse event rates, joint reconstruction involves real clinical risks:
- Venous thromboembolism (deep vein thrombosis or pulmonary embolism), managed via mechanical compression and pharmacologic thromboprophylaxis.
- Superficial wound dehiscence or deep prosthetic joint infection.
- Arthrofibrosis (excessive intra-articular scar formation), potentially requiring closed manipulation under anesthesia.
- Rare structural complications, including implant loosening, periprosthetic fractures, or localized neurovascular traction injuries.
The Phased Architecture of Rehabilitation
The surgical procedure provides an anatomically aligned joint, but functional outcomes depend on structured physical therapy:
- Acute Phase (Weeks 0 to 2): Priority centers on controlling localized edema through targeted cryotherapy, achieving complete passive knee extension (zero degrees), stimulating quadriceps motor control via isometric sets, and mastering safe ambulation with a walker or crutches.
- Intermediate Phase (Weeks 3 to 6): Emphasis moves toward progressive active-assisted flexion (aiming for 110 degrees or more), neuromuscular re-education, gait normalization without assistive devices, and gentle stationary cycling.
- Late Phase (Weeks 7 to 12 and Beyond): Focus transitions to eccentric muscular strengthening, dynamic balance training, closed-kinetic-chain loading, and progressive resumption of low-impact functional activities.
Patient adherence to daily home exercise protocols is a critical determinant of final range of motion and overall satisfaction.
Evaluating the Economic Structure of Joint Replacement
The total financial commitment for orthopedic surgery encompasses distinct medical categories. Patients evaluating costs should review:
- Institutional Facility Fees: Operating suite charges, sterile instrumentation processing, inpatient room tiers, and specialized nursing services.
- Professional Medical Fees: Surgeon, surgical assistant, and anesthesiologist billing.
- Prosthetic Implant Costs: Pricing variables associated with specialized metallurgy, cross-linked polyethylene inserts, and advanced robotic-assisted navigation platforms.
- Pre-Admission Workups: Outpatient imaging sequences, clinical laboratory panels, and specialized physician clearances.
- Post-Discharge Rehabilitation: Outpatient physical therapy visits spanning several months alongside durable medical equipment.
- Regional Pricing Models: Wide geographic variations exist across municipal, domestic, and international healthcare jurisdictions.
Patients must request transparent, comprehensive, and itemized fee schedules prior to making scheduling decisions.
Criteria for Selecting an Orthopedic Center of Excellence
Choosing an orthopedic surgical team should be guided by objective performance metrics:
- Surgical Volume Benchmarks: High-volume joint reconstruction surgeons—those completing over 100 to 150 joint procedures annually—statistically demonstrate lower revision and complication rates.
- Infection Control Indicators: Review documented institutional surgical site infection rates and air-filtration standards within operating suites.
- Integrated Care Pathways: Prioritize institutions that utilize coordinated teams comprising orthopedic surgeons, specialized anesthesiologists, and in-house orthopedic physical therapists.
- Clinical Transparency: Trustworthy clinical teams transparently discuss personal complication rates, realistic mobility expectations, and detailed postoperative escalation plans.
Traveling for Orthopedic Care: Logistics and Safety
Patients who travel for joint reconstruction—whether to specialized national centers or international medical destinations—require clear protocols to manage cross-border care:
- Remote Digital Review: Secure transmission of DICOM-format imaging and clinical records allows surgical teams to confirm procedural candidacy before travel begins.
- Thromboembolism and Travel Timing: Sitting stationary in aircraft cabins elevates thromboembolic risks following major lower-extremity surgery. Surgeons generally recommend remaining in the treatment region for at least 10 to 21 days for suture management, early rehabilitation, and travel clearance.
- Logistical Infrastructure: Selecting hospitals with dedicated international patient departments ensures language translation, accessible transportation, and coordinate continuity of care.
- Continuity Upon Return: Before traveling, patients must secure a domestic physical therapist and primary care clinician to oversee extended rehabilitation and manage any late-onset postoperative concerns.
Clinical Case Studies: Real-World Orthopedic Decision-Making
Treatment pathways are shaped by precise anatomical and functional parameters. The following hypothetical clinical examples demonstrate how specialists evaluate surgical candidates.
Case 1: Unicompartmental Degeneration in an Active Patient
Hypothetical Case: A 55-year-old construction manager presents with worsening right medial joint line pain over three years. Diagnostic weight-bearing radiographs show severe medial joint space collapse, yet the lateral compartment and patellofemoral joints exhibit pristine joint spacing. Magnetic resonance imaging confirms intact anterior and posterior cruciate ligaments with zero lateral pathology. Having exhausted unloader bracing and physical therapy, the surgeon and patient elect a medial unicompartmental knee replacement. By preserving the cruciate ligaments and lateral compartment, the patient achieves rapid recovery of functional kinematics.
Case 2: Advanced Tricompartmental Osteoarthritis with Varus Deformity
Hypothetical Case: A 72-year-old retired clerk presents with severe bilateral joint stiffness, night awakening, and a fixed 12-degree varus (bow-legged) deformity. Radiographic analysis confirms complete tricompartmental bone-on-bone articulation with extensive osteophyte formation. Due to multi-compartment involvement and structural mechanical deviation, partial resurfacing is contraindicated. The patient undergoes a total knee replacement utilizing computer-assisted navigation to realign the mechanical axis. Following a disciplined 12-week rehabilitation protocol, the patient regains functional, stable ambulation.
Common Clinical and Patient Missteps
- Prolonging Ineffective Injections: Receiving repeated intra-articular steroid injections indefinitely can risk subchondral bone health and tissue integrity without altering underlying structural disease.
- Severe Muscular Deconditioning Prior to Surgery: Delaying intervention until quadriceps atrophy and fixed contractures develop significantly complicates postoperative physical therapy.
- Underestimating Rehabilitation Demands: Assuming the surgical implant guarantees function without disciplined, progressive daily physical therapy.
- Relying Solely on Online Testimonials: Choosing medical centers based on marketing claims rather than objective surgical volumes, infection statistics, and verified clinician credentials.
- Early Resumption of High-Impact Loading: Subjecting a newly resurfaced prosthetic joint to high-impact distance running or ballistic pivoting risks premature polyethylene wear and early implant loosening.
Ten Crucial Questions to Ask an Orthopedic Specialist
- Which anatomical compartments of my knee joint are worn, and what is the severity of the cartilage loss?
- Have I exhausted every conservative and pharmacological treatment option appropriate for my stage of arthritis?
- Am I an appropriate candidate for a partial joint replacement, or does my anatomy require a total knee replacement?
- What is your annual surgical volume for this specific procedure?
- Which implant system, fixation method, and bearing material do you plan to use, and why?
- What are the most common perioperative risks for a patient with my specific medical profile?
- What modern pain management and regional anesthesia protocols do you implement to facilitate early mobilization?
- What specific functional criteria must I achieve prior to discharge from the surgical facility?
- When can I safely return to driving, non-sedentary work, and low-impact recreational activities?
- What specific physical therapy protocol and follow-up consultation schedule will I follow during the first six months?
Comparison Table
| Treatment Modality | Primary Mechanism | Clinical Benefits | Inherent Limitations | Ideal Patient Profile |
| Conservative Therapy | Mechanical offloading, strengthening, and inflammation reduction | Completely non-invasive; retains biological tissue; zero perioperative risks | Does not restore lost cartilage; therapeutic ceiling in advanced disease | Mild to moderate osteoarthritis, early cartilage wear, or medically fragile patients |
| Knee Arthroscopy | Minimally invasive intra-articular debridement or mechanical repair | Keyhole portals; outpatient delivery; rapid initial recovery | Ineffective for generalized bone-on-bone arthritis; addresses focal soft tissue only | Patients with discrete mechanical locking, meniscus tears, or loose articular fragments |
| Partial Knee Replacement | Selective prosthetic resurfacing of a single compartment | Preserves biological cruciate ligaments and bone stock; natural joint kinematics | Inapplicable to multi-compartment disease; secondary disease can develop in untreated zones | Severe degenerative disease strictly isolated to one compartment with intact ligaments |
| Total Knee Replacement | Comprehensive resurfacing of all three articular zones | Corrects structural alignment; eliminates generalized bone-on-bone friction | Major orthopedic procedure; demands disciplined multi-month physical rehabilitation | Advanced multi-compartment arthropathy, severe deformity, or failed conservative therapy |
Practical Tips
- Record Functional Baselines: Document specific mobility restrictions—such as maximum walking distances and stair-climbing limitations—to provide concrete metrics for your surgeon.
- Optimize Muscular Conditioning: Engaging in targeted pre-surgical physical therapy (pre-hab) improves quadriceps activation and accelerates postoperative mobility.
- Prepare the Recovery Environment: Eliminate household tripping hazards, install temporary bathroom support rails, and organize single-level living arrangements prior to hospital admission.
- Commit to Prescribed Rehabilitation: Active compliance with range-of-motion and strengthening drills is the primary determinant of long-term functional mobility.
- Vet Surgical Centers Objectively: Base your healthcare choices on procedural volume, documented infection rates, and the presence of dedicated orthopedic care teams.
Frequently Asked Questions (FAQs)
1. What primary clinical markers indicate that knee replacement surgery is necessary?
Surgeons consider arthroplasty when diagnostic imaging shows advanced joint space loss and the patient experiences severe functional limitations—such as difficulty walking, sleep-disrupting pain, and persistent joint stiffness—that remain unresolved after conservative care.
2. What is the expected mechanical lifespan of a modern knee prosthesis?
Contemporary total knee implants utilizing highly cross-linked polyethylene and advanced alloy surfaces demonstrate survivorship rates exceeding 15 to 20 years in the majority of patients, provided the joint is protected from high-impact trauma.
3. What clinical differences distinguish total from unicompartmental knee replacement?
Total knee arthroplasty resurfaces the medial, lateral, and patellofemoral compartments while often resecting the anterior cruciate ligament. Unicompartmental replacement resurfaces only one damaged compartment, preserving healthy native bone and all stabilizing cruciate ligaments.
4. How soon after orthopedic joint replacement does ambulation begin?
Under modern enhanced recovery pathways, physical therapists assist patients into a standing position and guide their first steps using a walker within hours of surgery or by the next morning.
5. How is postoperative pain managed during the acute recovery window?
Pain is controlled through multimodal protocols combining preoperative medications, local periarticular infiltration, regional nerve blocks, scheduled non-opioid analgesics, cryotherapy, and minimal oral narcotics, allowing early engagement in rehabilitation.
6. Can advanced bone-on-bone joint disease be reversed without surgical intervention?
Articular cartilage lacks the blood supply necessary for spontaneous structural regeneration. Non-surgical modalities can manage swelling and strengthen surrounding muscles, but they cannot restore eroded cartilage surfaces in advanced disease.
7. How long does a patient need to continue formal physical therapy?
Formal outpatient physical therapy generally lasts between 8 and 12 weeks. Following this period, patients transition to a structured, independent home exercise program for several months to build long-term muscular strength and joint stability.
8. What variables dictate the overall cost of knee replacement surgery?
Total expenses depend on surgical complexity, the specific implant manufacturer and design, facility operating suite fees, professional surgical and anesthesia charges, diagnostic imaging, and post-discharge physical therapy sessions.
9. When can international medical travel patients safely fly after joint reconstruction?
Most orthopedic surgeons recommend delaying long-distance air travel for 10 to 21 days after surgery. This waiting window allows surgical wounds to stabilize, sutures to be evaluated, and deep vein thrombosis risks to subside.
10. What specific activities are discouraged following a knee arthroplasty?
Surgeons advise against chronic, high-impact activities such as long-distance jogging, plyometrics, and contact sports to minimize component wear. Low-impact activities—including swimming, cycling, walking, and golf—are strongly encouraged.
Conclusion
Knee replacement surgery is a highly refined orthopedic intervention engineered to resolve persistent joint pain and restore functional mobility when conservative measures have failed. Achieving an optimal clinical outcome requires a clear understanding of joint mechanics, careful consideration of total versus partial procedures, and an unwavering commitment to postoperative physical rehabilitation. By familiarizing yourself with diagnostic criteria, implant designs, and recovery milestones, you can actively participate in treatment decisions alongside your healthcare team. Educational platforms like KneeHospitals.com serve as a helpful resource for understanding these orthopedic concepts, researching specialized facilities, and connecting with experienced surgical providers. Consult a board-certified orthopedic surgeon to evaluate your individual joint anatomy and identify the most appropriate treatment pathway for your mobility goals.
Leave a Reply