Inside Urological Care: A Healthcare Specialist Guide to Modern Treatments
Introduction
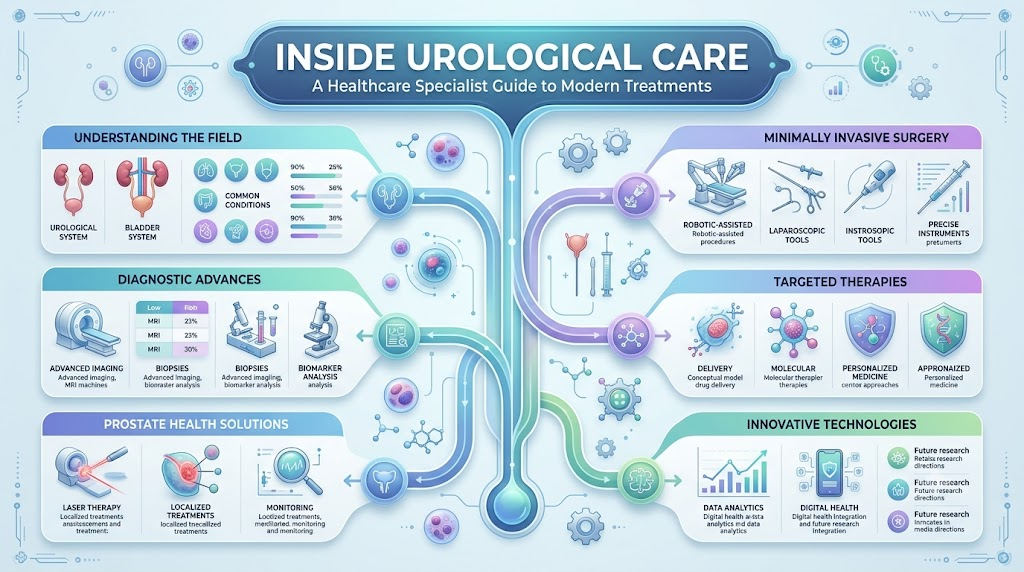
In clinical practice, urologists frequently meet individuals who have endured disruptive urinary symptoms for months before seeking advice. Hesitation often stems from uncertainty about the underlying cause or apprehension regarding medical examinations. The urinary tract and male reproductive structures carry out essential physiological functions, filtering metabolic waste, regulating fluid balance, and sustaining reproductive health. When disruptions occur within these organ systems, timely clinical evaluation is essential to prevent secondary complications. Approaching urological health from a clinical care perspective helps clarify the medical decision-making process. Understanding how physicians diagnose disorders, evaluate risk factors, and determine therapeutic pathways transforms what can feel like an intimidating medical journey into a clear, manageable process. This guide provides an inside look at how clinicians evaluate urological conditions, select appropriate therapies, utilize surgical technology, and partner with patients to achieve long-term health.
The Clinical Foundation: Anatomy and System Dynamics
The urological system encompasses the upper urinary tract—the kidneys and ureters—and the lower urinary tract, comprising the bladder and urethra. In men, the reproductive structures, specifically the prostate, seminal vesicles, and testes, share physical pathways and vascular networks with the urinary organs.
Because these components function as an integrated hydraulic system, pathology in one area directly impacts adjacent structures:
- An obstruction within a narrow ureter creates retrograde hydrostatic pressure, leading to hydronephrosis and impaired renal filtration.
- Tissue proliferation within the central zone of the prostate constricts the urethral lumen, forcing the bladder detrusor muscle to exert higher pressures to evacuate urine.
- Chronic low-grade bladder inflammation can alter nerve sensitivity throughout the pelvic floor, causing widespread discomfort.
Urological conditions affect individuals of all demographics. Clinicians approach these issues by evaluating whether a problem is obstructive, infectious, inflammatory, functional, or oncological in origin.
How Clinicians Categorize Symptoms
During a clinical consultation, a physician categorizes subjective symptoms into diagnostic patterns:
- Storage symptoms (irritative): Urgency, increased daytime frequency, and nocturia. These often suggest detrusor overactivity, localized infection, mucosal irritation, or bladder outlet obstruction.
- Voiding symptoms (obstructive): Hesitancy, weak urinary stream, intermittency, and straining. These indicate mechanical resistance or compromised detrusor contractility.
- Flank and abdominal pain: Acute, spasmodic flank discomfort radiating to the groin (renal colic) points toward upper tract obstruction, such as a calculus. Dull, persistent suprapubic pain often indicates lower tract distension or inflammation.
- Hematuria: Gross hematuria (visible blood) or microscopic hematuria (detected on urinalysis) demands systematic investigation. Clinicians consider it a potential indicator of malignancy, calculi, infection, or vascular anomalies until proven otherwise.
- Post-micturition symptoms: Sensation of incomplete emptying or post-void dribbling, pointing to functional or anatomical residual volume.
Diagnostic Workup and Clinical Reasoning
Clinicians rely on a step-by-step diagnostic sequence to narrow differential diagnoses, avoiding unnecessary testing while ensuring critical pathology is not overlooked.
Clinical History & Examination
           │
           ▼
Urinalysis & Baseline Serum Panels (Creatinine, BUN, PSA if indicated)
           │
           ▼
Initial Imaging (Renal/Bladder Ultrasound or Non-Contrast CT)
           │
           ▼
Specialized Investigations (Cystoscopy, Urodynamics, or MRI)
           │
           ▼
Multidisciplinary Treatment Strategy Formulated
Clinical History and Physical Examination
The consultation begins by establishing symptom chronicity, fluid balance habits, past medical history, and medication profiles. Objective examinations include abdominal palpation for organomegaly, a digital rectal exam to assess prostate symmetry and firmness in men, or targeted pelvic exams in women to evaluate organ prolapse.
Laboratory Workups
- Urinalysis with microscopic evaluation: Identifies erythrocytes, leukocytes, nitrites, and crystalluria, establishing whether an infection or inflammatory process is active.
- Urine culture and sensitivity: Pinpoints specific bacterial isolates to direct targeted antimicrobial therapy.
- Renal functional panels: Measures serum creatinine and glomerular filtration rates to gauge overall renal health.
- Prostate-Specific Antigen: Evaluated alongside age, prostate size, and clinical findings to assess glandular activity.
Imaging Modalities
- Ultrasound imaging: Evaluates kidney architecture, detects parenchymal thinning or hydronephrosis, and measures post-void residual urine volumes without ionizing radiation.
- Computed Tomography: Non-contrast helical CT scans serve as the gold standard for identifying stone location and density. Contrast-enhanced scans provide precise staging for tissue abnormalities.
- Multi-parametric MRI: Offers soft-tissue resolution for targeted prostate assessment and staging.
Endoscopic and Functional Tests
- Diagnostic cystoscopy: Allows direct visual inspection of the urethral mucosa, prostate configuration, and bladder urothelium.
- Urodynamic evaluation: Measures bladder pressure and flow rates to differentiate between muscle weakness and physical obstruction.
Core Treatment Philosophies in Urology
Modern urological therapy prioritizes preserving healthy tissue, protecting renal function, and minimizing procedural recovery times. Clinicians evaluate four primary intervention categories:
1. Structured Conservative Care
Watchful waiting and active surveillance are distinct clinical choices, not passive inaction. In stable conditions or low-risk malignancies, scheduled periodic monitoring—using imaging, lab panels, and clinical checkups—avoids the functional side effects of immediate procedural intervention while preserving the window for curative treatment if disease progression occurs.
2. Medical Management
Prescription regimens target underlying physiological mechanisms:
- Alpha-adrenergic antagonists: Relax smooth muscle at the bladder neck and prostate to relieve urinary resistance.
- 5-alpha reductase inhibitors: Inhibit hormonal pathways to halt or reverse glandular tissue enlargement over several months.
- Anticholinergic agents and beta-3 agonists: Modulate detrusor contractions to address urge incontinence.
- Evidence-based antimicrobials: Eradicate pathogens based on laboratory sensitivity testing.
3. Endourology and Minimally Invasive Procedures
Advances in endoscopic miniaturization allow urologists to navigate natural urinary channels:
- Laser fragmentation: Uses holmium or thulium lasers to pulverize urinary stones.
- Transurethral resections and ablations: Removes obstructive tissue internally with minimal recovery periods.
- Extracorporeal Shock Wave Lithotripsy: Employs external acoustic waves to fragment stones without surgical incisions.
4. Surgical Interventions
When conservative and endoscopic measures are insufficient, reconstructive or extirpative surgery is required. Surgeons choose between traditional open approaches, conventional laparoscopy, or robotic-assisted surgery based on anatomical complexity, patient health, and oncological objectives.
Clinical Management of Common Conditions
Kidney Calculi Protocols
Physicians determine kidney stone management based on size, location, composition, and whether an infection is present:
- Expectant therapy: Stones under 5 mm in asymptomatic patients without infection are monitored for spontaneous passage, supported by hydration and pain relief.
- Extracorporeal Shock Wave Lithotripsy: Used for non-complex upper pole or renal pelvis stones under specific density thresholds.
- Ureteroscopy with laser lithotripsy: The standard intervention for mid-to-distal ureteral calculi and intrarenal stones, using flexible scopes and laser fibers.
- Percutaneous Nephrolithotomy: Indicated for large or complex staghorn calculi, accessing the renal collecting system directly through a flank tract.
Benign Prostatic Hyperplasia
Treatment decisions for BPH are guided by objective symptom scores and bladder emptying efficiency:
- Lifestyle adjustments and pharmacotherapy: The first step for mild-to-moderate obstruction, focusing on fluid timing and targeted oral medications.
- Minimally invasive tissue modification: Office or outpatient procedures (such as water vapor ablation or prostatic urethral lifts) provide structural relief with low risks to sexual function.
- Surgical de-obstruction: Transurethral Resection of the Prostate (TURP) or laser enucleation (HoLEP) removes larger volumes of obstructing adenoma tissue to restore normal urinary flow.
Prostate Malignancy Protocols
Prostate oncology care depends on disease stratification:
- Active surveillance: Recommended for localized, low-grade tumors, utilizing scheduled PSA tracking, periodic MRIs, and repeat biopsies.
- Radical prostatectomy: Complete surgical excision of the prostate and seminal vesicles, frequently utilizing robotic platforms to preserve surrounding neurovascular bundles.
- Radiation therapy: Delivered via external beam techniques or brachytherapy to destroy neoplastic cells.
- Systemic therapies: Androgen deprivation therapy, chemotherapeutics, and targeted therapies manage metastatic or locally advanced disease.
Urinary Tract Infections
A methodical clinical approach prevents chronic recurrence and antibiotic resistance:
- Diagnostic confirmation: Relies on clean-catch cultures to guide targeted antibiotic selection rather than broad-spectrum empirical therapy.
- Anatomical screening: Recurrent infections warrant ultrasound or cystoscopy to evaluate for anatomical abnormalities, urinary stasis, or persistent calculi.
Bladder Cancer Management
Bladder tumors are managed according to stage and depth of tissue invasion:
- Transurethral Resection of Bladder Tumor (TURBT): Serves as both the initial diagnostic biopsy and the primary therapeutic resection for superficial lesions.
- Intravesical instillation: Therapeutic agents (such as BCG or chemotherapy) are placed directly into the bladder to decrease recurrence in non-muscle-invasive cases.
- Radical cystectomy and reconstruction: The standard for muscle-invasive disease, requiring complete bladder removal followed by urinary reconstruction (such as an ileal conduit or neobladder).
The Surgeon’s Perspective on Robotic Systems
Robotic systems serve as an extension of the surgeon’s hands, not an autonomous operating tool.
Surgeon Console Control
  │
  ├─ 3D High-Definition Visualization (Up to 10x magnification)
  ├─ Tremor Filtration & Motion Scaling
  └─ Multi-Jointed EndoWrist Instruments (Exceeding human wrist articulation)
           │
           ▼
Precise Operative Execution at the Patient Bedside
Robotic platforms offer significant technical benefits during delicate dissections, such as sparing neurovascular bundles during prostatectomy or excising renal tumors while preserving remaining kidney tissue. However, surgical outcomes ultimately depend on the training, volume, and judgment of the operating surgeon, alongside appropriate patient selection.
Evaluating Hospital Infrastructure and Care Teams
When considering advanced care, patients benefit from evaluating specific facility capabilities:
- Surgical and case volume: Medical centers that routinely perform high volumes of specific urological procedures consistently demonstrate lower complication rates and more refined post-operative recovery protocols.
- Diagnostic infrastructure: Access to on-site frozen section pathology, dedicated urodynamic laboratories, and high-resolution MRI scanners accelerates precise treatment planning.
- Multidisciplinary clinical boards: Complex oncological cases should be evaluated through tumor boards that bring together urologists, radiation oncologists, medical oncologists, and pathologists.
- Postoperative and emergency support: Facilities must maintain 24-hour urological coverage to manage unexpected complications, retention events, or urgent post-procedural needs.
Treatment Modality Comparison
| Clinical Approach | Common Indications | Key Strengths | Limitations & Risks |
| Observation & Surveillance | Small asymptomatic stones; low-risk prostate tumors | Avoids procedural side effects; maintains baseline anatomy | Demands consistent compliance with monitoring schedules |
| Pharmacological Care | Mild-to-moderate BPH; acute infections; overactive bladder | Non-invasive; easily adjusted; preserves physical structures | Ongoing medication dependency; potential systemic side effects |
| Endoscopic Laser Procedures | Obstructive ureteral stones; superficial bladder lesions | Utilizes natural anatomical pathways; minimal downtime | May require temporary internal stent placement |
| Robotic-Assisted Surgery | Localized prostate tumors; complex partial nephrectomy | Enhanced precision; smaller incisions; reduced blood loss | Requires general anesthesia; reliant on surgeon experience |
| Open Reconstructive Surgery | Extensive pelvic pathology; severe anatomical trauma | Direct operative field access; versatile reconstructive capability | Longer recovery times; larger surgical incisions |
Practical Clinical Scenarios
Scenario 1: Acute Calculus Obstruction
A 38-year-old software developer develops sudden, severe left flank pain, vomiting, and diaphoresis. An urgent unenhanced CT scan reveals a 6 mm stone lodged in the proximal ureter, causing moderate hydronephrosis. Because the stone is large enough to have a lower probability of spontaneous passage, the urologist recommends an outpatient ureteroscopy. Using a laser fiber, the specialist fragments the stone and places a temporary stent. The patient experiences immediate pain relief, and the stent is removed one week later.
Scenario 2: Diagnostic Evaluation for Hematuria
A 55-year-old former smoker notices painless, pink-tinged urine over two days. Rather than assuming the issue is an infection, the individual consults a urology specialist. The physician orders a multiphase CT urogram alongside a flexible cystoscopy. While the upper tracts are clear, the cystoscopy identifies a solitary 1.5 cm papillary lesion on the posterior bladder wall. A timely TURBT confirms a low-grade, non-muscle-invasive tumor. A single post-operative dose of intravesical chemotherapy is delivered, followed by a routine surveillance schedule.
Scenario 3: Navigating Prostate Enlargement Treatment Decisions
A 67-year-old retired teacher experiences chronic urinary frequency and an interrupted flow that disrupts sleep. His IPSS score indicates severe symptoms, and urodynamics confirm significant bladder outflow resistance. After discussing the trade-offs of long-term medication versus intervention, he chooses transurethral water vapor therapy. The minimally invasive procedure is performed under light sedation, successfully relieving his obstruction while preserving his urinary continence and lifestyle.
A Step-by-Step Approach to Treatment Planning
- Document symptom patterns: Track voiding frequency, urgency episodes, fluid intake, and the specific nature of any discomfort.
- Undergo complete diagnostic staging: Ensure laboratory, imaging, and functional testing are completed before deciding on irreversible treatments.
- Review all therapeutic options: Discuss watchful waiting, medical therapies, and surgical options with your specialist.
- Evaluate personal risk tolerance: Weigh the potential side effects of daily medication against the recovery timelines of procedural interventions.
- Verify provider experience: Assess your surgeon’s specific procedure volume, complication rates, and institutional facility support.
- Obtain second opinions for complex pathology: Confirm oncological staging or major reconstructive treatment plans through an independent specialist.
- Commit to long-term follow-up: Attend all scheduled post-procedure screenings, laboratory panels, and surveillance imaging appointments.
Common Clinical Pitfalls to Avoid
- Dismissing transient hematuria: Painless blood in the urine can resolve spontaneously even when underlying pathology remains active.
- Treating symptoms without a diagnosis: Taking repeated courses of antibiotics without confirming an infection can delay necessary care for stones, interstitial cystitis, or tumors.
- Equating high-tech tools with surgical skill: Advanced surgical platforms cannot compensate for poor case selection or inexperienced surgical execution.
- Neglecting urinary retention: Chronic partial retention stretches the bladder wall over time, leading to irreversible detrusor muscle failure and renal back-pressure.
- Skipping follow-up after stones pass: Identifying why a stone formed through metabolic urine testing is essential to prevent painful recurrences.
Essential Questions for Your Urology Consultation
- What specific physiological condition is causing my symptoms?
- Which tests are strictly diagnostic, and which are needed to plan treatment?
- What are the clinical benefits and potential side effects of each treatment option?
- What are the medical risks if I choose active monitoring rather than immediate intervention?
- How many procedures of this exact type does your clinical team perform annually?
- What is the typical recovery process, including work restrictions and stent discomfort?
- What are the statistical risks of recurrence or long-term complications for this condition?
- Are there dietary adjustments or behavioral modifications that support long-term management?
- Which specific post-procedure warning signs require emergency medical attention?
- Does my diagnosis warrant review by a specialized multidisciplinary care board?
Key Takeaways
- Early intervention preserves organ function: Timely treatment of obstructions protects long-term bladder and kidney health.
- Hematuria requires prompt evaluation: Any visible or microscopic blood in the urine demands formal diagnostic assessment.
- Treatments are tailored to individual health: Care plans depend on exact anatomical findings, symptom severity, and overall patient health.
- Surgical success relies on clinical experience: Robotic tools offer valuable precision, but surgeon training remains the primary factor in good outcomes.
- Follow-up prevents recurrence: Managing chronic urological conditions requires ongoing post-treatment monitoring and healthy daily habits.
Frequently Asked Questions
What does a urologist treat?
A urologist is a medical specialist who diagnoses and manages disorders of the urinary tract in men and women, including the kidneys, ureters, bladder, and urethra. They also treat conditions affecting the male reproductive organs, such as the prostate, testes, and associated structures.
When should someone seek a urological consultation?
You should seek a consultation if you notice blood in your urine, severe flank pain, chronic urinary tract infections, difficulties initiating or maintaining urination, urinary incontinence, abnormal PSA test results, or unexplained testicular swelling or discomfort.
How are kidney stones diagnosed?
Physicians diagnose kidney stones using unenhanced, low-dose computed tomography (CT) scans or renal ultrasounds. These imaging studies identify the size, number, and location of stones, while urine and blood tests evaluate kidney function and screen for concurrent infections.
What treatments are available for kidney stones?
Treatment depends on stone size and location. Small stones are often managed with hydration and pain relief. Larger or symptomatic stones may require Extracorporeal Shock Wave Lithotripsy, ureteroscopy with laser fragmentation, or percutaneous nephrolithotomy.
What are common treatments for an enlarged prostate?
Enlarged prostate treatments range from lifestyle changes and medications to minimally invasive office-based therapies and surgical procedures like transurethral resection of the prostate (TURP) or laser enucleation.
How is prostate cancer treated?
Prostate cancer care plans are individualized based on tumor risk category, stage, and patient health. Approaches include active surveillance for low-risk disease, robotic radical prostatectomy, radiation therapy, and systemic treatments for advanced cases.
What causes visible blood in the urine?
Hematuria can stem from urinary tract infections, kidney or bladder stones, enlarged prostate tissue, trauma, or benign and malignant growths in the kidneys, ureters, or bladder. Prompt professional evaluation is always recommended to identify the cause.
What is robotic urology surgery?
Robotic urology surgery is a minimally invasive laparoscopic technique where a surgeon controls high-precision robotic arms and miniature instruments through a console. It provides high-definition 3D visualization and enhanced articulation for intricate procedures like prostatectomies and partial nephrectomies.
How do I choose an appropriate urology hospital?
Evaluate hospitals based on their diagnostic imaging capabilities, procedural volume for your specific condition, intensive care support, availability of specialized urologists, dedicated emergency urology services, and integrated multidisciplinary care teams.
How can I find an experienced urologist?
Search for certified urologists practicing at accredited medical centers within your area. Confirm their experience with your specific diagnosis, review insurance compatibility, check hospital affiliations, and consult reputable directories to review provider credentials.
Conclusion
Navigating urological care requires clear communication, comprehensive diagnostics, and an understanding of available clinical pathways. Urological health influences essential physical functions that directly affect daily comfort and long-term well-being. By viewing your health through an informed, step-by-step clinical lens, you can better understand your symptoms, evaluate treatment options, and make collaborative decisions with your healthcare team. Partnering with experienced specialists and accredited facilities ensures that medical and surgical decisions remain grounded in safety, precision, and personalized care.
Leave a Reply